AnCan GU ASCO26 survivorship poster: participants strongly endorse our Groups
For release on Monday, Feb 23, 2026
AnCan Foundation strongly believes we run the best support groups available!! We can now release the first results of our 2024 AnCan Participant Survey that confirms that our participants think so too. This first batch of results is taken from almost 300 prostate cancer responses at all levels of disease.
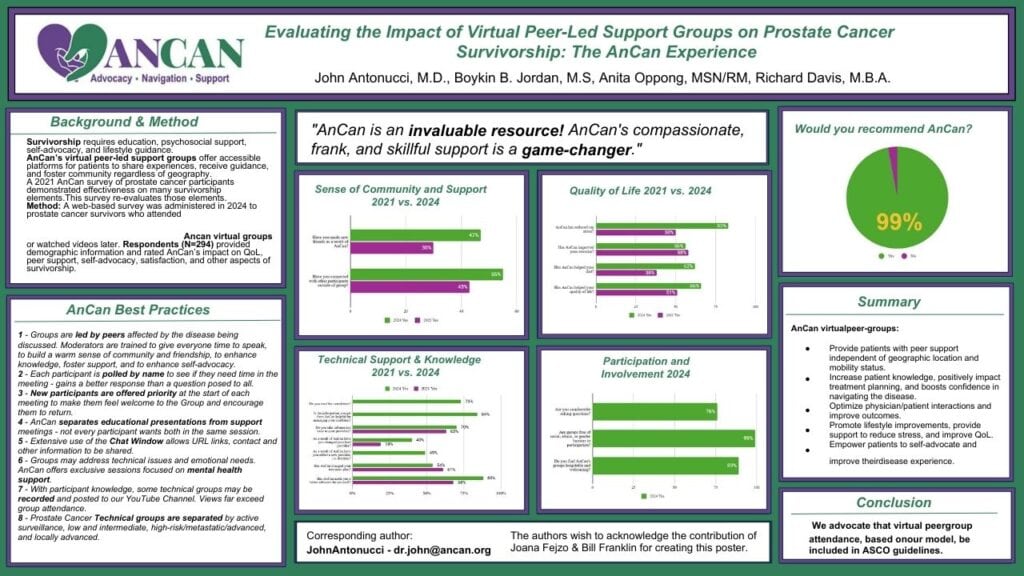
99% of respondents would recommend AnCan Groups
66% improved Quality of Life – 83% noted reduced stress; 62% improved nutrition; 56% increased exercise
88% advocated better for themselves and AnCan influenced over half (54%) the treatment paths
47% made new friendships – AnCan’s personal favorite since this extends support well beyond our Groups
If you’re attending GU ASCO26 , please stop by our poster on Friday, Feb 27 to meet Dr. John Antonucci, discuss these astonishing results and the AnCan method, and pick up a flyer of the poster.
Evaluating the impact of virtual peer-led support groups on prostate cancer survivorship: the AnCan experience.
John Antonucci*, Boykin B. Jordan, Anita Oppong, Richard Davis
Abstract Number: 265
Poster Board Number: A23
Session Title: Poster Session B: Prostate Cancer and Urothelial Carcinoma
Date and Time: February 27, 2026, 11:30 AM-12:45 PM; 4:45 PM-5:45 PM (PST)
Background: Comprehensive prostate cancer (PCa) survivorship requires more than just clinical care, including education, psychosocial support, self-advocacy, and lifestyle guidance—needs often unmet by traditional oncology visits. Virtual peer-led support groups, such as those offered by the AnCan Foundation, offer accessible, real-time platforms for patients to share experiences, receive guidance, and foster community, regardless of geography. This study evaluates the impact of AnCan participation on factors known to be associated with a better quality of life (QOL) among PCa survivors.
Methods: A web-based survey was administered in 2024 to PCa survivors who attended or expressed interest in AnCan meetings. Respondents (N=294) provided demographic information and rated AnCan’s impact on QOL, peer support, self-advocacy, and satisfaction. Data were analyzed to assess the subjective influence of AnCan’s virtual support model on survivorship.
Results: (2021 results are in brackets for comparison.) Most respondents were in their 60s–70s (75%), highly educated (82%), and 55% had incomes over $100,000. Eighty-three percent had someone in their lives they could rely on and with whom they maintained regular contact.
Nearly all (97%) found AnCan meetings helpful for disease understanding, learning options, and well-being. Sixty-six percent reported improved QOL; 83% [50%] noted reduced stress; 62% [38%] improved nutrition; and 56% [58%] increased exercise. Satisfaction was high, with 99% recommending AnCan.
AnCan involvement enhanced self-advocacy (88%), improved patient-provider communication, and improved decision-making. Seventy percent brought information from AnCan to their providers, 49% added new providers, and 40% changed their lead provider. Over half (54%) reported that AnCan influenced their treatment path.
Socially, 55% [43%] connected with peers outside meetings, and 47% made new friendships.
Conclusions: Survey responses indicate that the AnCan virtual peer-led model, to be described in the poster, meaningfully increases patient knowledge, empowers self-advocacy, reduces stress, and fosters healthy behaviors, improving quality of life for PCa survivors. We advocate for integrating such peer support into NCCN, AUA, and ASCO survivorship guidelines.
As some of you may know, the liberal telehealth rules to conduct medical appointments remotely that were enabled during Covid, sunsetted late last year. AnCan was upset and vocal that many of our patient advocacy organizations active on The Hill did not campaign more widely to extend it. Organizations like ZERO (prostate cancer) have significant and expensive government relations groups precisely to address such issues on behalf of us patients. AnCan had to bring it to ZERO’s attention to move the ball at a time when ZERO’s high paid CEO was self-admittedly sleeping on the switch.
Telehealth was temporarily extended for those living in rural areas. Then one of our newly minted prostate cancer Moderators, David Sharpe, brought it to AnCan’s attention that legislation was passed on Feb 3, 2026 that has extended comprehensive telehealth through the end of 2027. We asked David to blog its welcome return to wider availability and tell his story around telehealth – thank you Mr. Sharpe!
Medicare Telehealth Coverage Is Extended
The federal government has restored Medicare coverage for telehealth until the end of 2027. That means you can now possibly consult with your doctors online rather than having to meet with them in-person.
Why did I say possibly? Because state medical licensing laws still apply. Often, they can undermine your doctor’s ability to join you on the call. Here’s why: (Don’t construe the following comments as legal or medical advice. This is general information only.)
Telehealth consultations are easiest to arrange when a patient and doctor are in the same state. For instance, if you live in Springfield, Illinois, and want to have a virtual chat with an oncologist in Chicago, no legal impediments are likely to stand in your way.
Things can get tougher if the doctor practices in another state. Physicians are typically required to be licensed in the state where the patient is physically located during the consult. Therein lies a common problem: the doctor is licensed in one state, and you’re in another.
But loopholes exist. According to the Center for Connected Health Policy (CCHP), “A few states have licenses or telehealth-specific exceptions that allow an out-of-state provider to render services via telemedicine in a state where they are not located, or allow a clinician to provide services via telehealth in a state if certain conditions are met (such as agreeing that they will not open an office in that state). Still other states have laws that don’t specifically address telehealth and/or telemedicine licensing, but make allowances for practicing in contiguous states. . . .” For specifics about your state’s rules, explore CCHP’s handy state-by-state guide: https://www.cchpca.org/topic/cross-state-licensing-professional-requirements/.
Despite those exceptions, many physicians and medical centers require patients to be in the same state as the doctor during telehealth appointments. I wish I’d known that last year, before trying to set up virtual consultations from my home in Portland, Oregon, with Fred Hutch (Washington), UCSF, City of Hope (both California), and MD Anderson (Texas0—all of whom turned me down. Oregon Health & Science University (OHSU, Oregon)) would have refused, too, if I had been in any other state.
But some physicians and hospitals were more relaxed about it. Despite remaining in Portland, I wrangled a telehealth visit with a UCLA specialist. Two AnCan buddies of mine in Oregon and Arizona did so as well. I had even better luck with out-of-state doctors in community practices. Two agreed to confer with me online, and one declined.
If you live near—but not in—the state where your doctor practices, perhaps the easiest option is to make a run for the border. One AnCan member has adopted that strategy as a convenient means of communicating with his faraway medical team in an adjacent state while also satisfying the legal requirements. To have that meeting, he travels a few miles from home to a casino just across the state line; the casino lets him conduct telehealth consultations there. That approach shaves hours off what would otherwise be a protracted road trip to talk with his doctors face-to-face. # # #
AnCan thanks the following sponsors for making this recording possible: Novartis, Telix, Blue Earth Diagnostics and Foundation Medicine.
Views expressed in this Recording are solely the opinion of AnCan Foundation, our Moderators and Participants.
AnCan does not accept sponsored promotion. Any drugs, protocols or devices discussed are based solely on anecdotal peer experience or clinical evidence.
AnCan cannot and does not provide medical advice. We encourage you to discuss anything you hear in our sessions with your own medical team.
AnCan reminds all Participants that Adverse Events experienced from prescribed drugs or protocols should be reported to the pharmaceutical manufacturer or the FDA Adverse Event Reporting System (FAERS). To do so call 1-800-332-1066 or download interactive FDA Form 3500 https://www.fda.gov/media/76299/download
All AnCan’s groups are free and drop-in … join us in person sometime! You can find out more about our 12 monthly prostate cancer meetings at https://ancan.org/prostate-cancer/ Sign up to receive a weekly Reminder/Newsletter for this Group or others at https://ancan.org/contact-us/
Join our other free and drop in groups:
Men (Only) Speaking Freely…1st & 3rd Thursdays @ 8.00 pm Eastern https://ancan.org/men-speaking-freely/
Veterans Healthcare Navigation… 1st & 3rd Tuesdays @ 8.00 pm Eastern Schmier Room https://ancan.org/veterans/
Veterans Speaking freely… 4th Tuesday @ @ 8.00 pm Eastern Schmier Room
Editor’s Pick: Pros & Cons of Estradiol (E2) as primary and complementary ADT… & mustard!
Topics Discussed
Intraductal (ICC-P) AND cribriform complicate treatment decision for younger Gent; more IDC-P & crib man recurs after RP bringing questionable treatment from Kwon; young denovo Mx BRCA2 has surgery then salvage RT and HT; knee surgery results in temporary daro suspension; mustard under the tongue; Dana Farber gives better advice and recommends GUNS RT trial; a great candidate for ‘Playing the Long game’; extensive discussion around the use of estradiol (E2), both as primary ADT and as complementary to LHRH ADT drugs
Jim Marshall, Veteran, Alexandria, VA sent: 8:12 PM
Need to ask your VA Doctor. I doubt if there is a VA policy on this, Jim Marshall
Brian Haack – Eagle, ID sent: 8:20 PM
great discussion on E2. See you next week
Bruce Schrimpf sent: 8:21 PM
AMEN!!!! It is very enjoyable to be on nothing!!!
Jeffrey G sent: 8:27 PM
To anyone: Has there been discussion of becoming castration resistant on E2?
scott b sent: 8:31 PM
thank you… great discussion!
Bruce Schrimpf sent: 8:41 PM
So why does not “medical science” search for the cause and the cure for prostate cancer? We are screwing around with surgery, radiation and hormone therapy that is not a cure for prostate cancer all the while doctors, “medical facilities,” and big pharma that cut, radiate, and pontificate make money on selling what is essentially rubbish.
(Editor’s Note: that’s exactly what pharma/biopharma is seeking, Bruce. To date we can only find drugs that manage and not cure it!)
AnCan thanks the following sponsors for making this recording possible: Novartis, Telix, Blue Earth Diagnostics and Foundation Medicine.
Views expressed in this Recording are solely the opinion of AnCan Foundation, our Moderators and Participants.
AnCan does not accept sponsored promotion. Any drugs, protocols or devices discussed are based solely on anecdotal peer experience or clinical evidence.
AnCan cannot and does not provide medical advice. We encourage you to discuss anything you hear in our sessions with your own medical team.
AnCan reminds all Participants that Adverse Events experienced from prescribed drugs or protocols should be reported to the pharmaceutical manufacturer or the FDA Adverse Event Reporting System (FAERS). To do so call 1-800-332-1066 or download interactive FDA Form 3500 https://www.fda.gov/media/76299/download
All AnCan’s groups are free and drop-in … join us in person sometime! You can find out more about our 12 monthly prostate cancer meetings at https://ancan.org/prostate-cancer/ Sign up to receive a weekly Reminder/Newsletter for this Group or others at https://ancan.org/contact-us/
Join our other free and drop in groups:
Men (Only) Speaking Freely…1st & 3rd Thursdays @ 8.00 pm Eastern https://ancan.org/men-speaking-freely/
Veterans Healthcare Navigation… 1st & 3rd Tuesdays @ 8.00 pm Eastern Schmier Room https://ancan.org/veterans/
Veterans Speaking freely… 4th Tuesday @ @ 8.00 pm Eastern Schmier Room
Editor’s Pick: Cribriform complicates treatment decision; and we discuss NCI trial
Topics Discussed
Over-70 KP ‘Couple’ insisted on PSA against protocol and found 4+4 cancer – cribriform complicates Tx decision; recently Dx denovo Mx ‘Couple’ seeking their way; recurrence after 7 years may set up well for NCI trial; high Decipher and cribriform may point to doublet; NCI Playing the Long Game discussed – Dr. Paul rightly finds it antithetical; Natera trial result reports zero level ctDNA; leg pain after starting doublet HT; push the IHT 3 more months with diligent AS; estradiol vets defer conversation to next week; side effects of radiation treatment
Is Gallium – 68 the more sensitive recommended radioactive tracer to use for a PSMA-PET Scan? Just wondering if seeking the best tracer produces better results.
AnCan thanks the following sponsors for making this recording possible: Novartis, Telix, Blue Earth Diagnostics and Foundation Medicine.
Views expressed in this Recording are solely the opinion of AnCan Foundation, our Moderators and Participants.
AnCan does not accept sponsored promotion. Any drugs, protocols or devices discussed are based solely on anecdotal peer experience or clinical evidence.
AnCan cannot and does not provide medical advice. We encourage you to discuss anything you hear in our sessions with your own medical team.
AnCan reminds all Participants that Adverse Events experienced from prescribed drugs or protocols should be reported to the pharmaceutical manufacturer or the FDA Adverse Event Reporting System (FAERS). To do so call 1-800-332-1066 or download interactive FDA Form 3500 https://www.fda.gov/media/76299/download
All AnCan’s groups are free and drop-in … join us in person sometime! You can find out more about our 12 monthly prostate cancer meetings at https://ancan.org/prostate-cancer/ Sign up to receive a weekly Reminder/Newsletter for this Group or others at https://ancan.org/contact-us/
Join our other free and drop in groups:
Men (Only) Speaking Freely…1st & 3rd Thursdays @ 8.00 pm Eastern https://ancan.org/men-speaking-freely/
Veterans Healthcare Navigation… 1st & 3rd Tuesdays @ 8.00 pm Eastern Schmier Room https://ancan.org/veterans/
Veterans Speaking freely… 4th Tuesday @ @ 8.00 pm Eastern Schmier Room
Editor’s Pick: Unrelated Newbies from either Coast have almost identical issues.
Topics Discussed
Our two Newbies are ‘twins’ – both denovo Mx on the cusp between high and low volume mets, and both with less experienced GU med oncs; 4x chemo down doing well with a full head of hair!; finding an exercise program; contacting NCI; Orgovyx trumps a 6-mo. depot shot; early radiation cystitis; finding Dr. E; with heart history, Orgovyx or Lupron?; discussing NCI trial & adaptive therapy
Chat
AnCan – Rick sent: 5:55 PM
Technical assistance 877 582 7011
AnCan – Rick sent: 5:56 PM
Playing the Long Game https://www.youtube.com/watch?v=v4jzyAeOtNI
Great Meeting again gang! I’m out – time to walk the dog.
michael perillo sent: 7:21 PM
Hi all, need to leave the meeting. Obviously have quite a bit of work to do re possible change to orggovyx, possible use of radiation, chemo or other triplet approach, possible somatic testing as well as second opinion. Will follw up on future meetings. Thanks Michael
AnCan–John A sent: 7:21 PM
Ok Michael, welcome
Eric James; Tyler TX sent: 7:25 PM
The weight you use is relative to your strength. Weight is usually selected based on how many reps you are to do.
Steve Schuler (Go Seahawks!) sent: 7:31 PM
Did you have doubling time data before going on the ADT?
The reason I ask is that there will be a lag after going off ADT before the DT data will be reliable
Eric James; Tyler TX sent: 7:33 PM
The NCI doc presentation has some overlap with Adaptive Therapy
Steve Schuler (Go Seahawks!) sent: 7:38 PM
Orgovyx will restore your T faster once you get off it
RJ Smith (Seattle) sent: 7:48 PM
ChatGPT, etc.) is not a GU Med Onc. Not even a urologist or MD of any kind.
Steve Schuler (Go Seahawks!) sent: 7:56 PM
gotta drop, love to hear more discussion of the NCI YT video at some point. If that happens after I drop, I’ll view the recording of this session later
Richard B, Silver Spring, MD sent: 8:02 PM
I need to step away due to an early start tomorrow morning. Nothing new to report but more assessments this week. So possible report next week. ‘Appreciate all the conversations. Good night.
dan-s alexandria sent: 8:03 PM
gotta go, gents…. good conversations.
Bruce Schrimpf sent: 8:11 PM
As always it was very informative. Thanks for being “there” for those of us struggling through!
AnCan has long been perplexed by the prostate cancer category “non-metastatic Castrate Resistant” or even “non-metastatic Hormone Sensitive”. If PSA is rising after primary treatment but prior to hormone treatment, something’s going on, however, ‘micro-metastatic’. It’s like being just a little bit pregnant!!
This paper considers a new category, PSMA Positive Biochemically Recurrent – PSMA+ BCR. We circulated the paper to our Brains Trust and reached out to Dr. Ravi Madan at the National Cancer Institute (NCI) with a couple of questions. Dr Madan offered to meet with us along with his colleague, Dr. Melissa Abel. What resulted was this REMARKABLE video that could present many of our recurrent and advanced AnCan (& non-AnCan) participants with one of the most mind-blowing videos many have seen in a long time,
DO YOU REALLY NEED TREATMENT??
As the venerable and highly respected Dr. Paul Schellhammer said in the meeting, “it’s like listening 15 years ago to the folks who began to promote active surveillance ( in first line treatment)” Dr. Madan and Dr. Abel have collected solid data from around 150 patients that suggests men with slow PSA doubling times can “play the long game” as Dr. Ravi calls it, and defer active treatment when their disease recurs.
PLEASE watch this astonishing presentation, listen to some excellent observations and questions, and consider how it relates to your own situation. And spread the word to others. Dr. Madan’s and Dr. Abel’s NCI clinical trial can be found at https://www.clinicaltrials.gov/study/NCT05588128. Don’t immediately assume you’re not eligible before speaking with them… but you’ll have to watch the video to get their contact information.